
The Breathing Test You've Probably Never Heard Of (And Why It Matters)
What a PFT Actually Tells Your Doctor
I recently learned that I have been breathing wrong for 52 years.
I did not know this was a category of wrong you could be. I assumed breathing was like blinking: automatic, free, and not subject to professional review. Then my doctor said the words “Pulmonary Function Test,” and I said, “Is that the thing where they check whether I’m the kind of person who can fill a birthday balloon?” And she said, “Sort of.”
That is the most accurate description of a PFT I have ever heard, and it came from a man who once tried to inflate a pool toy with a leaf blower.
A PFT, short for Pulmonary Function Test, sounds like a Cold War spy agency. (“Our man in Vienna reports that the PFT has been compromised.”) It is actually just you, a machine, and a technician who is cheerful in a way that should be studied. The technician will ask you to blow as hard as you possibly can, and he or she will mean it, and you will do it, and then you will be asked to do it again.
Here is what nobody tells you going in: a PFT is not one test. It is several tests, stacked together like a medical Russian nesting doll, each designed to find out something different about your lungs. Let’s go through them.
Test #1: Spirometry, Or “The Balloon the Size of a Buick”
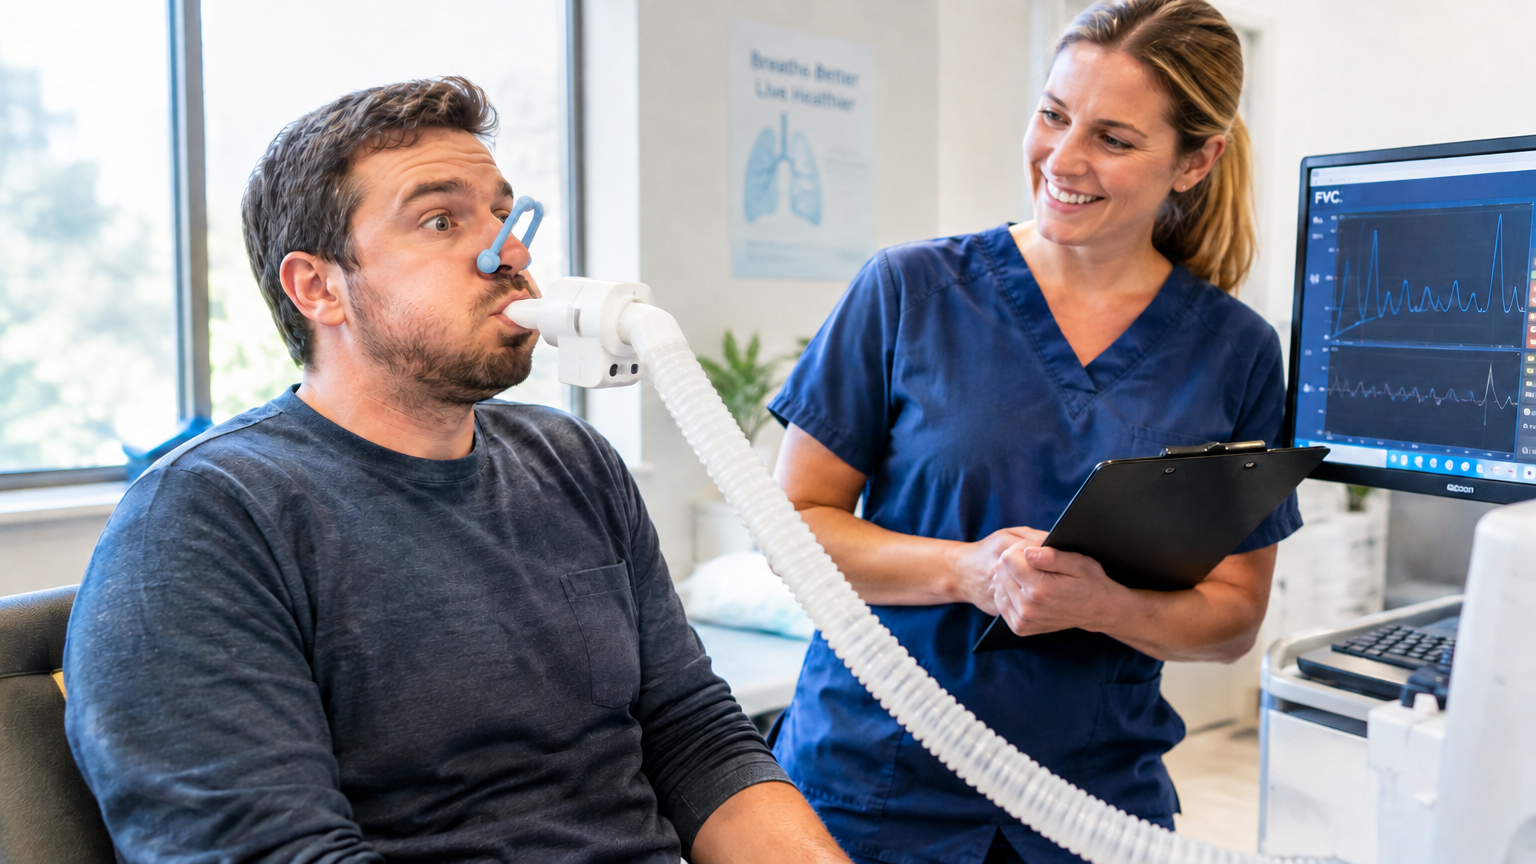
You sit in a chair that looks like it was borrowed from a dentist’s office that gave up on dentistry. A clip goes on your nose, because the machine does not trust your nostrils to stay out of this. You are handed a tube, and the technician says, “Take the deepest breath of your life, then blow it all out as hard and fast as you can, and keep going, keep going, KEEP GOING.”
“Keep going” lasts about six seconds. From the inside, where your lungs are collapsing like a bouncy castle at the end of a birthday party, it feels like the length of a presidential administration. (Any administration. Pick your favorite. It doesn’t matter.)
They will ask you to do this at least three times, and sometimes as many as eight. This is not because they enjoy watching you turn colors. It is because the machine wants consistent, repeatable results, and your first attempt is usually your worst. On attempt one you’re thinking about the nose clip, the tube, and whether anybody in the waiting room can see your face. By attempt four, you have achieved what the medical profession calls “a good effort” and what I call “surrender.”
Here’s the part that makes it useful. The machine measures two big things: how much air you can blow out in total, and how much of it you can blow out in the first second. Those two numbers are known as FVC and FEV1, which look like something you’d find on a license plate in Nebraska but together tell your doctor a lot about how open your airways are and how well your lungs move air.
Sometimes they’ll then give you a puff of a medication to open your airways and have you blow again, to see whether anything improves. If it does, that tells your doctor something important. This is the only test in your life where getting a better score the second time is a medical clue instead of a character flaw.
Test #2: Lung Volumes, Or “The Human Snow Globe”
Here things escalate. You may be asked to sit inside something called a body plethysmograph, a clear box about the size of a phone booth. (If you don’t remember what those were, ask someone over 50. They will tell you about it for forty-five minutes.) I call it the Human Snow Globe, and the experience of sitting in one is somewhere between a science experiment and a very small, very beige car wash.
Its job is to measure how much air your lungs can really hold, including the air that never leaves. Doctors call that “residual volume.” I call it the junk drawer. Every lung has one: a certain amount of air that just sits there, forever, doing nothing, next to a dead flashlight and eleven soy sauce packets. Learning that you have a junk drawer in your chest is weirdly comforting. Learning that everyone does is better.
Your technician will have you breathe normally and then pant against a little shutter while you hold your own cheeks with your hands. I am not making this up. You will look exactly like a pug who has been told a secret. No one will take a picture. Probably.
Test #3: Diffusion Capacity, Or “Ten Seconds That Last a Decade”
This one measures how well oxygen actually crosses from the air sacs in your lungs into your bloodstream. You breathe in a small, harmless mixture of gas, and then you hold it for about ten seconds while the machine checks your work.
Ten seconds does not sound like a long time. But ten seconds while holding your breath, strapped to medical equipment, aware that a stranger is grading you, is the emotional equivalent of a decade in federal prison. You will hold that breath like it owes you money. You will think thoughts. You will remember things you said in 1994.
And then it is over, and you realize you have just participated in a test of the lung’s plumbing, which is the sort of sentence nobody ever expects to say about themselves at 9:15 on a Tuesday.
A Brief Q&A For the Terrified
Q. Will it hurt?
A. No. Nothing is injected. Nothing is inserted anywhere it has no business being. The worst-case scenario is mild, temporary lightheadedness and the humbling discovery that you can no longer blow out a candle the way you did at thirty-five.
Q. How long does it take?
A. About half an hour, though the technician will say “almost done” a number of times that is mathematically impossible.
Q. Will they yell at me?
A. They will coach you. Loudly. With enthusiasm. It’s like being cheered on by a very supportive air-traffic controller.
Q. Is it a scary test?
A. No. The scary part is the Googling you did the night before.
Q. Are you a senior citizen?
A. If so, please note that the technician will say “Great job!” after every single attempt, including the one where you laughed and ruined it.
So What Is the Point of All This?
Here’s the sincere part, and I promise to be brief, because I can hear the Human Snow Globe laughing at me.
A PFT does not diagnose you on its own. What it does is give your pulmonologist the shape of the problem. Think of it as a floor plan of your breathing.
If air has trouble getting out, because the airways are narrowed, like a garden hose somebody is standing on, that is called an obstructive pattern. It’s what doctors see in conditions like asthma and COPD.
If your lungs can’t fully expand, because they’re stiff or smaller than they should be, that is called a restrictive pattern. It can show up with conditions such as pulmonary fibrosis and other lung diseases.
And if the numbers on the diffusion test are low, it tells your doctor that the handoff of oxygen into your blood may be struggling, which points them toward a different set of questions entirely.
Your results are compared against what’s expected for someone your age, height, and sex. That’s how your doctor tells asthma from COPD from fibrosis from “you’re fine, stop googling your cough at 2 a.m.” (You’ll do it anyway. We all do.)
This matters for one very simple reason: lung problems are sneaky. They don’t kick the door in. They move in quietly, take a little bit of your stamina each year, and let you explain it away. I’m just out of shape. It’s the stairs. It’s the humidity. It’s Georgia in pollen season and everyone coughs. A PFT can catch a problem before you’ve rearranged your entire life around it, and the sooner you know what’s going on, the more your doctor has to work with.
How To Not Embarrass Yourself
A few tips from a man who has been through it:
- Ask your doctor’s office about prep. You may be told to skip certain inhalers beforehand, avoid smoking, or not eat a giant meal. Do not wing it. Call.
- Wear comfortable clothes. Nobody has ever said “I really wish I’d worn the belt” during a lung test.
- Give it everything you’ve got. The test depends on your effort. The numbers can only be as good as the blow, so don’t be shy. Nobody is judging you. (Okay, the Human Snow Globe is. A little.)
- Don’t panic if you cough or feel lightheaded. It’s common, and it passes. Tell the technician and take a break.
- Bring your questions. The results are only useful if you and your doctor talk about them.
The Takeaway
Your lungs have been quietly working in the background for your entire life. They have never asked for a vacation. They have never taken a sick day. They ask for nothing but oxygen and the occasional deep breath, and they have put up with your cardio plans, your campfires, and that one summer you tried to learn the trumpet.
The least you can do is let somebody check in on them.
So if your doctor orders a PFT because of a nagging cough, shortness of breath on the stairs, a smoking history, or just a feeling that something about your breathing has been “off” for longer than you want to admit out loud, go. It takes about half an hour. It will not hurt. And it is one of the best tools your doctor has to see what your lungs are actually doing, instead of guessing from the outside, which is the medical equivalent of judging a book by whether it makes you cough.
You’ve been breathing for 52 years, or however many you’ve got.
You might as well find out how it’s going.
If you’ve had unexplained shortness of breath, a lingering cough, or a referral for a PFT, the physicians and providers at Athens Pulmonary & Sleep Medicine can walk you through exactly what to expect and what your results mean. Schedule a consultation today.









